NATUROPATHIC GUIDELINES FOR CUTTING CHOLESTEROL

Cholesterol levels have become the source of much fear, even though cholesterol is one of the most valuable substances in the human body. Cholesterol is needed for strong cell walls, as a precursor for hormone production, and as a coating around nerves. There are two sources of cholesterol in the body: (1) that which is obtained from the diet; and (2) that which is produced in the body (primarily from the liver). 

HDL cholesterol (i.e., high–density lipoprotein) is considered to be beneficial – it works to carry cholesterol away from the blood and back to the liver where it can be processed and removed from the body. LDL cholesterol (i.e., low–density lipoprotein), however, is generally thought to be harmful to the body – it carries cholesterol into the bloodstream and can place it into the lining of the arterial walls, thereby promoting atherosclerosis. Cholesterol can create a problem when levels in the blood are too high; generally, high cholesterol is defined as levels that are greater than 200 mg/dl. The naturopathic approach to reducing cholesterol levels includes a combination of lifestyle, dietary, and supplement recommendations. 

LIFESTYLE RECOMMENDATIONS 

  • Regular aerobic/moderate exercise 
  • Regular exercise contributes to higher levels of HDL cholesterol and reduces the risk of heart disease 
  • Yoga or qigong for relaxation and improved blood circulation 
  • Minimize stress 
  • Get adequate amounts of daily sunlight – a lack of sunlight has been shown to adversely affect cholesterol levels 
  • Weight reduction (if appropriate) 


DIETARY RECOMMENDATIONS 

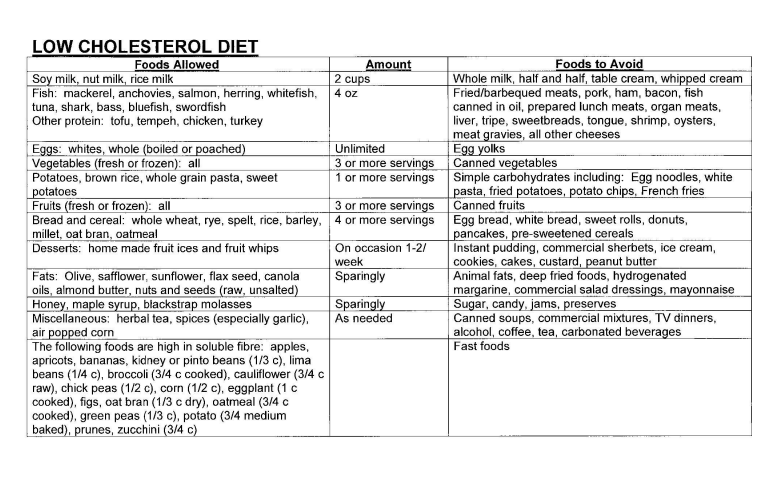
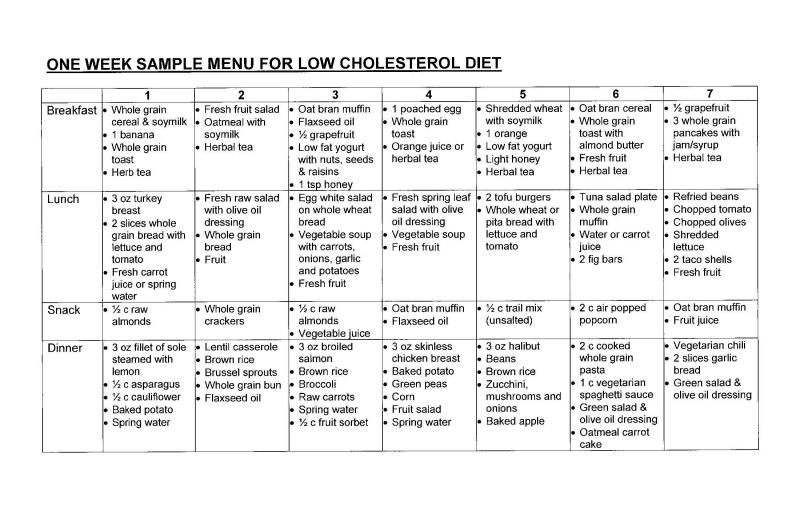
  • Eat a high fiber, low fat, low cholesterol diet 
  • Reduce or eliminate animal products and other sources of saturated fats e.g., red meats, eggs, dairy products, palm oil, coconut oil 
  • Increase fruits, vegetables, grains, and legumes 
  • Reduce sugar and salt intake
  • Calorie percentages for reducing cholesterol should be as follows: 70% complex carbohydrates – e.g., brown rice, oats, millet, beans
  • 12-15% protein – e.g., tofu, beans, fish
  • 15-18% fat – e.g., fish, olive oil, flaxseed oil, nuts, seeds
  • Reduce cholesterol in the diet to less than 300 to 400 mg daily
  • Consider occasional short fasts – e.g., once a month, fast on Spirulina, carrot, and celery juice (or lemon and water) 


Therapeutic Foods & Supplements: 

Oat bran and brown rice bran – these are the best foods for lowering cholesterol 

Apples, bananas, carrots, grapefruit, celery, dried beans (especially navy, pinto, and kidney beans), garlic, olive oil, and cold water fish (salmon, herring, mackerel) – these are also cholesterol–lowering foods 

Barley, beans, flaxseeds, brown rice, fruits, and oats – such foods contain water–soluble fiber which is beneficial in reducing cholesterol 


Ground Flax Seeds 

Grind whole seeds in coffee grinder (cleaning grinder well each time) and add to cereal, yogurt or smoothies 

2 Tablespoons provides adequate fiber per day For more 

information 

on the multi–benefits of Flax, check this website http://www.whfoods.com/genpage.php?tname=foodspice&dbid=81 


Spirulina 

spirulina is a form of blue–green algae that is rich in beta–carotene, iron and B complex vitamins. When taken on a daily basis, Spirulina has been shown to decrease cholesterol levels Raw unsalted almonds 

almonds are rich in the amino acid arginine which has been shown to decrease cholesterol within a four–week period 


Green tea 

regular intake of green tea has been shown to decrease LDL and total cholesterol levels while increasing HDL 

for maximum benefits, one should drink at least 3 cups daily of whole leaf green tea 


Other beneficial foods include: 

omega 6 fatty acids – evening primrose oil, flaxseed oil (also contains omega 3 fatty acids), black current oil, and other vegetable/nut/seed oils 

о liquid chlorophyll, alfalfa sprouts, buckwheat, watercress 


Niacin 

onions, beans, legumes, soy, ginger, yogurt 

Fresh juice made with any combination of the following: carrot, beet, celery, pineapple, parsley, alfalfa, spinach, asparagus, chlorophyll and honey. Note: Carrot juice helps to flush out fat from bile in the liver and this helps to lower cholesterol. 

о Niacin is well established as being effective in the treatment of high cholesterol levels – 

specifically, it reduces total cholesterol, LDL cholesterol, and triglycerides while increasing HDL 


Guggullipid 

Guggullipid is the standardized extract of the mukal tree (Commiphora mukal) which is native to India 

Several clinical studies have confirmed its ability to lower both cholesterol and triglyceride levels Typically, total cholesterol will drop 14-27%, LDL by 15-35%, triglycerides by 22-30%, and HDL will increase by 16-20% with 12-36 weeks of supplementation 

The effect of guggullipid on cholesterol and triglyceride levels is comparable to that of lipid- lowering drugs but without the side–effects 

Mechanism of action: guggullipid increases the liver’s metabolism of LDL 

Other benefits: it has been shown to prevent the formation of atherosclerosis and aid in the reversal of atherosclerotic plaques in animals 


Policosanol 

Balances cholesterol levels by impacting both excessive manufacture and impaired breakdown of cholesterol levels. 

Policosanol has been shown to reduce both total cholesterol and LDL cholesterol levels, also shown to effectively decrease cholesterol levels in tissues like the heart, liver and fatty tissue. Policosanol can be used as an alternative to aspirin as an anti–platelet agent. Policosanol is also a powerful antioxidant. 


References: Textbook of Natural Medicine by Pizzorno & Murray. Churchill Livingstone: 1999; Textbook of Nutritional Medicine by Werbach. Thrid Line Press, Inc: 1999

A New Comprehensive Review: Cholesterol Is Not the Root Cause of Heart Disease

Key Highlights

  • Comprehensively reviews more than six decades of cardiovascular research, synthesizing approximately 280 peer-reviewed publications evaluating ten major lipid and lipoprotein biomarkers in atherosclerotic cardiovascular disease (ASCVD).
  • Reinterprets the six-decade evolution of lipid biomarkers, arguing that the progression from total cholesterol to LDL-C, ApoB, LDL particle number (LDL-P), small dense LDL (sdLDL), oxidized LDL (oxLDL), and lipoprotein(a) [Lp(a)] reflects increasingly refined measurements of downstream biology rather than the discovery of the fundamental root drivers of ASCVD.
  • Challenges the conventional lipid-centric paradigm by concluding that most major lipid biomarkers function primarily as exposure biomarkers or intermediate pathogenic mechanisms, rather than universal root drivers of disease.
  • Identifies lipoprotein(a) [Lp(a)] as the lipid biomarker with the strongest evidence for an inherited causal contribution, while concluding that it functions as a partial upstream causal contributor rather than a universal root cause.
  • Applies an Integrative Orthomolecular Systems Medicine (IOM) perspective to distinguish upstream biological drivers, intermediate pathogenic mechanisms, biomarkers, and clinical manifestations, providing a more integrated interpretation of lipid biology and ASCVD.
  • Integrates five complementary domains of scientific evidence-physiology, pathophysiology, epidemiology, genetics, and randomized clinical trials-to reassess the biological roles of LDL-C, ApoB, LDL-P, sdLDL, oxLDL, triglycerides (TG), HDL-C, and Lp(a).
  • Explains why improving lipid biomarkers does not, by itself, establish root causation. Although lipid-lowering therapies can reduce cardiovascular events, substantial residual cardiovascular risk persists, suggesting that important upstream biological disturbances remain unaddressed.
  • Calls for a paradigm shift-from the continual search for increasingly sophisticated lipid biomarkers toward identifying the upstream biological drivers of ASCVD through an Integrative and Systems Medicine framework focused on true root-cause prevention.

Why Has Cardiovascular Medicine Kept Changing Lipid Biomarkers?

For more than sixty years, cholesterol has occupied center stage in cardiovascular medicine. During this period, researchers have introduced an increasingly sophisticated array of lipid biomarkers in an effort to improve cardiovascular risk assessment and better understand the biology of atherosclerosis. The field evolved from total cholesterol to LDL cholesterol, and later to apolipoprotein B (ApoB), LDL particle number (LDL-P), small dense LDL (sdLDL), oxidized LDL (oxLDL), and renewed clinical interest in lipoprotein(a) [Lp(a)].

Each new biomarker represented genuine scientific progress. Each improved cardiovascular risk prediction. Each addressed important limitations of the biomarkers that came before it.

Yet this remarkable history raises a question that has received surprisingly little attention.

Why has cardiovascular medicine repeatedly needed a new “best” lipid biomarker?

If each successive biomarker represented the true root cause of atherosclerosis, why has the field continued searching for another, and then another?

In medicine, long-term prevention and, where possible, durable disease reversal generally depend on understanding and addressing the upstream biological processes that initiate disease-not simply modifying intermediate pathogenic mechanisms or treating downstream clinical manifestations after they have developed. Identifying those upstream drivers is therefore essential for advancing true root-cause prevention.

For more than six decades, cardiovascular medicine has progressively refined measurements of downstream lipid biology without fully identifying the upstream biological drivers that initiate ASCVD.

A newly released MDPI Preprint, Beyond Cholesterol: A Comprehensive Integrative and Systems Medicine Reassessment of Lipid and Lipoprotein Biomarkers in ASCVD, takes an unconventional approach. Rather than comparing lipid biomarkers primarily according to their ability to predict cardiovascular risk, it asks a more fundamental question: What biological role does each biomarker play within the pathogenesis of ASCVD? To answer this question, the review synthesizes approximately 280 peer-reviewed publications spanning more than six decades of cardiovascular research.

The review reaches a provocative conclusion.

The continual evolution of lipid biomarkers does not necessarily reflect progressively deeper discoveries of the biological root causes of ASCVD.

Instead, it largely reflects progressively more refined measurements of the same downstream biological pathway.


Important Players-but Mostly Not the Root Cause

The review does not argue that lipid biology is unimportant.

Nor does it deny that lipid-lowering therapies can reduce cardiovascular events.

Rather, it proposes that the greatest limitation of the traditional lipid-centric paradigm is one of biological classification.

For decades, cardiovascular medicine has largely assumed that increasingly sophisticated lipid biomarkers would eventually identify the fundamental cause of atherosclerosis.

Our review suggests a different interpretation.

Most major lipid biomarkers are better understood as biomarkers of exposure or intermediate pathogenic mechanisms than as the upstream biological drivers that initiate vascular disease.

In other words, cardiovascular medicine has become increasingly successful at measuring and modifying lipid biology.

But lipid biology itself may not represent where ASCVD actually begins.

This distinction may help explain why decades of remarkable advances in lipid research have improved cardiovascular risk prediction without fully resolving the question of disease initiation.


A Different Way to Understand the Evolution of Lipid Biomarkers

The history of lipid research can be viewed as a continuing effort to improve the precision of cardiovascular risk assessment.

Total cholesterol proved helpful but lacked specificity.

LDL cholesterol provided better prediction.

ApoB more accurately reflected the number of circulating atherogenic particles.

LDL particle number further refined assessment of lipoprotein burden.

Small dense LDL and oxidized LDL improved understanding of plaque formation and vascular injury.

More recently, Lp(a) has emerged as an important genetically determined cardiovascular risk factor.

Viewed individually, each advance represents important scientific progress.

Viewed collectively, however, they tell a different story.

Rather than uncovering progressively deeper root causes of ASCVD, these biomarkers appear to describe different aspects of the same downstream biological pathway.

This observation forms one of the central conclusions of our review.

The question, therefore, may not be:

Which lipid biomarker is best?

Instead, the more fundamental question becomes:

Where does each biomarker fit within the disease process?

That simple shift in perspective changes how the entire field may be interpreted.


Understanding How ASCVD Develops

Integrated and System Medicine Framework for Major Lipid and Lipoprotein Biomarkers in ASCVD

One of the central conclusions of this review is that ASCVD should be understood as a biological process rather than explained by any single biomarker.

Instead of treating every lipid biomarker as a potential root cause, the review distinguishes four distinct components of disease development:

  • Upstream biological drivers
  • Exposure biomarkers
  • Intermediate pathogenic mechanisms
  • Clinical manifestations

Failure to distinguish these levels has contributed to decades of confusion.

A biomarker can predict disease extremely well without representing the earliest initiating cause.

Likewise, an intermediate pathogenic mechanism may contribute directly to plaque formation while still remaining downstream of more fundamental biological disturbances.

Recognizing these distinctions provides a more coherent Integrative and Systems Medicine framework for integrating physiology, pathophysiology, epidemiology, genetics, and randomized clinical trials.

More importantly, it suggests that the future of cardiovascular medicine may depend less on discovering yet another lipid biomarker and more on identifying the upstream biological disturbances that give rise to them in the first place.


Where Do the Major Lipid Biomarkers Fit?

To answer this question, the review systematically evaluates each major lipid biomarker using five independent domains of scientific evidence:

  • Normal physiology
  • Atherosclerotic pathophysiology
  • Epidemiological studies
  • Human genetics and Mendelian randomization
  • Randomized clinical intervention trials

Each addresses a different scientific question. No single line of evidence is sufficient by itself. Only by integrating all five can the biological role of each biomarker be properly understood.

The review concludes that the major lipid biomarkers occupy different positions within the overall disease process of ASCVD.

LDL-C, ApoB, and LDL Particle Number (LDL-P) primarily quantify cumulative exposure to circulating atherogenic lipoproteins. They are excellent exposure biomarkers and valuable therapeutic targets, but they do not appear to represent the universal initiating causes of vascular disease.

Small dense LDL (sdLDL) and oxidized LDL (oxLDL) participate directly in endothelial injury, foam-cell formation, oxidative stress, and plaque progression. Their biological role is more appropriately classified as intermediate pathogenic mechanisms.

Triglycerides (TG) and HDL cholesterol (HDL-C) largely reflect broader metabolic physiology, including insulin sensitivity, hepatic metabolism, and systemic energy regulation. They provide important information about metabolic health but are unlikely to function as independent root drivers of ASCVD.

Among all currently recognized lipid biomarkers, lipoprotein(a) [Lp(a)] stands apart. Human genetic studies consistently support an inherited causal contribution to cardiovascular risk. Nevertheless, our review concludes that even Lp(a) is best understood as a partial upstream causal contributor, rather than a universal explanation for atherosclerosis.

Taken together, these observations suggest that the major lipid biomarkers complement rather than compete with one another. Each provides valuable insight into a different stage of the disease process. However, with the partial exception of Lp(a), most function primarily as exposure biomarkers or intermediate pathogenic mechanisms rather than the upstream biological drivers that initiate ASCVD.


Why Lowering Lipids Does Not Necessarily Eliminate the Root Cause

One of the most important distinctions made in this review is the difference between therapeutic benefit and biological causation.

There is little doubt that lipid-lowering therapies have advanced cardiovascular medicine. Numerous clinical trials have demonstrated reductions in cardiovascular events with statins, ezetimibe, PCSK9 inhibitors, and other lipid-lowering approaches.

However, an important scientific question remains.

Does improving a biological pathway prove that the pathway is the original cause of disease?

History suggests otherwise.

Medicine frequently succeeds by modifying downstream mechanisms without completely correcting the upstream disturbances that initiated the disease.

Lowering blood glucose does not necessarily reverse insulin resistance.

Reducing blood pressure does not eliminate all of the biological factors responsible for hypertension.

Similarly, improving lipid profiles does not necessarily establish that lipid abnormalities are the earliest biological drivers of ASCVD.

Perhaps the strongest evidence supporting this distinction is the persistence of substantial residual cardiovascular risk despite increasingly intensive lipid-lowering therapy.

If lipid abnormalities represented the complete explanation for ASCVD, progressively more effective lipid lowering might be expected to eliminate most cardiovascular risk.

That has not occurred.

Instead, the persistence of residual risk suggests that important upstream biological disturbances remain active.


Looking Beyond Cholesterol

If most lipid biomarkers are not the earliest biological drivers of ASCVD, where should cardiovascular medicine focus next?

Our review suggests shifting greater attention toward upstream biological disturbances that precede lipid abnormalities and initiate vascular injury.

These upstream processes are likely multifactorial and interconnected. They may include metabolic dysfunction, insulin resistance, chronic inflammation, oxidative stress, endothelial dysfunction, impaired vascular repair, micronutrient insufficiency, environmental toxicant exposure, chronic infections, and other interacting biological processes.

From an Integrative Orthomolecular Systems Medicine (IOM) perspective, these upstream disturbances represent the biological terrain upon which lipid abnormalities subsequently develop.

Rather than replacing lipid biology, this broader systems perspective places lipid biomarkers within their appropriate biological context.

In this view, lipid abnormalities become important components of disease progression-but not necessarily the earliest initiating events.


A Paradigm Shift for Cardiovascular Medicine

For more than sixty years, cardiovascular medicine has pursued increasingly sophisticated lipid biomarkers in an effort to better understand ASCVD.

That effort has unquestionably advanced our understanding of vascular biology and improved cardiovascular risk assessment.

Our review, however, suggests that the continual evolution of lipid biomarkers also tells another story.

It suggests that cardiovascular medicine has become increasingly precise at measuring downstream biology while the upstream biological drivers of disease remain incompletely understood.

The next major breakthrough in ASCVD may therefore not come from discovering yet another lipid biomarker.

It may come from identifying the upstream biological disturbances that give rise to those biomarkers.

That shift-from managing downstream manifestations toward understanding upstream biological drivers-represents the central message of this comprehensive review.

The future of cardiovascular medicine should not abandon lipid biology.

Rather, it should place lipid biomarkers within the broader disease process, distinguishing upstream biological drivers from exposure biomarkers, intermediate pathogenic mechanisms, and clinical manifestations.

For more than sixty years, cardiovascular medicine has searched for increasingly sophisticated lipid biomarkers. Our review suggests that the next major breakthrough may not come from discovering another biomarker. It may come from identifying and correcting the upstream biological disturbances that give rise to them. This systems-based, root-cause approach lies at the heart of Integrative Orthomolecular Systems Medicine (IOM) and, ultimately, is what it means to move beyond cholesterol.


Reference

Cheng, R. Z. Beyond Cholesterol: A Comprehensive Integrative and Systems Medicine Reassessment of Lipid and Lipoprotein Biomarkers in ASCVD. Preprints 2026, 2026070008. https://doi.org/10.20944/preprints202607.0008.v1


Reader Discussion and Questions

OMNS welcomes comments, questions, ideas, experiences, and respectful dialogue from readers, patients, healthcare professionals, researchers, and students worldwide.

We encourage participation on OMNS Interactive, where the exchange of knowledge and perspectives helps advance understanding and foster meaningful discussion.

Join the conversation:
https://omns.substack.com


About OMNS Interactive

OMNS Interactive is the discussion and commentary platform of the Orthomolecular Medicine News Service (OMNS).

The original OMNS website remains the official archive of OMNS publications.

Subscribe to OMNS Interactive for future articles, commentary, and discussions:
https://omns.substack.com

Content is provided for educational purposes only and does not constitute medical advice.
The Nutritional Management of Anxiety


People with anxiety can have nutritional imbalances that contribute to their condition. Important nutritional factors for people with anxiety include:

  • Vitamin B3 metabolism
  • Histamine metabolism (especially low histamine)
  • Metal metabolism imbalance
  • Pyrrole disorder
  • Sugar imbalance
  • Essential fatty acid deficiencies
  • Cerebral (brain) allergies


Vitamin B3 (Niacin) Metabolism

A form of B3, Niacin, in appropriate sufficient doses, influences benzodiazepine and GABA receptor metabolism. The effect is reduced nerve cell excitability in the limbic (emotion) system which reduces anxiety. This is a commonly used therapy by orthomolecular/naturopathic practitioners in the treatment of anxiety. If you are currently taking a conventional benzodiazepine medication please discuss potential side effects and withdrawal dependence problems with your medical providers. Withdrawal symptoms from conventional benzodiazepines range from confusion, agitation and anxiety to psychosis in protracted cases. GABA receptor metabolism is occasionally disrupted by conventional benzodiazepine use. GABA receptors are influenced strongly by certain heavy metals in the body and balancing these metals nutritionally (see below) is important.

Histamine Metabolism

Histamine metabolism is associated with anxiety. What is histamine and why is it so important? Histamine is integral in balancing the electrical activity of the nucleus accumbens, which is the area of the brain responsible for behavioral responses, filtering incoming sensory information and communicating with the hypothalamus, ventral tegmentum and amygdala.¹ People with low histamine can have typical symptoms of anxiety, under-achievement and cyclic or suicidal depression.² These individuals often have food allergies and environmental allergies but they do not typically have seasonal allergies.³ They may have a history of learning disability, under-achievement, hyperactivity, paranoia, and nervousness.⁴ Excess copper levels and zinc deficiency, discussed below under heavy metal overload, are typical in low histamine profiles.⁵ These individuals do well with specific nutrients at appropriate doses.

Heavy Metal Metabolism Imbalance

Heavy metal imbalance is associated with anxiety, behavior disorder (including ADHD and OCD), depression and schizophrenia.⁶ Excess copper is common in patients with mental health imbalances.⁷ Nutritional supplementation can be used to eliminate heavy metals but patients also need to avoid certain foods and environmental exposure(s) that contain these metals.⁸

Pyrrole Disorder

What is pyrrole disorder and how is this related to brain function? In some people, one specific pyrrole – 2,4-dimethyl-3ethyl-pyrrole – is produced in excess.⁹ 2,4-dimethyl-3-ethyl-pyrrole interacts with key nutrients useful in normal brain function. The resultant nutrient deficiencies are associated with anxiety. What behaviors and physical and mental symptoms are associated with pyrrole imbalance? Pyrrole imbalance is a condition that effects the whole body with both physical and mental symptoms. Some specific behaviors and physical symptoms that have been associated with pyrrole imbalance are high internal tension, stress intolerance, unconstrained irritability, susceptibility to infection, fatigue, and abdominal pain to name a few.¹⁰ Nutritional therapy for this condition involves appropriate doses of supplements to compensate for key nutrient deficiencies.¹¹

Essential Fatty Acid (EFA) Deficiency

Anxiety, ADHD, depression and behavior disorders are benefited by appropriate EFA supplementation. EFA’s, especially omega 3, are good fats, not saturated with hydrogen, and unfortunately not readily provided in our diet. Neurons and brain tissue are in constant demand of these essential fats as they make up neuron cell borders. Clinical studies are showing successful interventions with specific EFA’s.

Cerebral (Brain) Allergies

Cerebral allergies involve a gut reaction that ultimately perpetuates the release of brain toxins resulting in imbalanced brain function, malaise, etc.¹² Culprit food and environmental compounds have to be ruled out in some cases of anxiety. An investigative procedure called elimination dieting and/or food intolerance testing is important for diagnosis. Individualized nutritional guidelines derived from lab assessment and patient history provide comprehensive dietary suggestions that can be essential in the management of anxiety. Candidiasis or gut microbe imbalances need to be ruled out because they can result in the release of neurotoxins. Parasitic insult with resultant toxin formation may also need to be addressed. Malabsorption also has to be ruled out.

Sugar Imbalance (Hypoglycemia)

Hypoglycemia is the term that describes low sugar in the blood. Irritability, poor memory, “late afternoon blues”, poor concentration, tiredness, cold hands and muscle cramping are typical hypoglycemic symptoms. Hypoglycemia tends to be an aggravating factor in mental illness rather than a causative factor. The nutritional protocol for hypoglycemia involves dietary changes and supplement support. It is said that hypoglycemia is 100% treatable in compliant patients- emphasizing the need to adhere to the diet. Mono-cropping of grains and resultant ‘saccharine diseases’ has led to serious problems in society today including anxiety and carbohydrate neuroses.¹³

Disclaimer: This information is for patient education and is not intended for self-prescription. The syndromes discussed here are complex requiring professional assessment and supervision by a licensed practitioner with strong foundations in nutritional (orthomolecular) medicine. Some patients require conventional treatment, some do better on nutritional treatment and some require a skillful combination of both. Prescribed drugs can safely be maintained for therapeutic interventions. Based on signs of clinical improvement, your medical practitioner can monitor drug withdrawal as this becomes another key component of recovery. Information herein is not intended for self prescription of self-diagnosis and is not intended to replace the advice of a medical practitioner or health-care provider. The information in this handout is an independent appraisal of the literature and is offered as information, not advice.

Adapted from: Copyright © 2002 by Raymond J. Pataracchia B.Sc., N.D. The Naturopathic Medical Research Clinic (N.M.R.C.), http://nmrc.ca/

References:

1. Shoblock & O’Donnell 2000; Otake & Nakamura, 2000; Chronister et al, 1982

2. Jackson, et al, 1998; Edelmen, 1996; Jaffe & Kruesi, 1992; Pfeiffer, 1988; Walsh, Ref. B

3. Walsh, 1997b

4. Walsh, 1997b

5. Sandstead, 1994; Wallwork, 1987; Pfeiffer & Braverman, 1982; Walsh, P.T.C.- Ref. B

6. Walsh, P.T.C.- Ref. C

7. Walsh, P.T.C. – Ref. B

8. Walsh, Ref. B

9. Jackson et al, 1997; Pfeiffer, 1975; Sohler et al, 1974

10. Edelman, 1996; Pfeiffer, 1975 11. Marz, 1997 12. Marz, 1997; Edelman, 1996

Copyright 2014 Natural Terrain Naturopathic Clinic. Dr. Christina Bjorndal

Elimination Diet: Foods You May Eat

Legumes (beans) – Includes soybeans, tofu, lentils, peas, chickpeas, navy beans, kidney beans, black beans, string beans, and others.

Vegetables – Use a wide variety. All vegetables except corn are permitted.

Proteins – Poultry and fowl, fresh fish, (such as tuna and salmon, packed in spring water). Shrimp and most canned or packaged shellfish (such as lobster, crab, oysters may contain sulfites and should be avoided. Canned tuna, salmon and other canned fish are OK. Beef and pork may be eaten unless specified otherwise. Lamb rarely causes allergic reactions, and may be used even when other meats are restricted. Also recommended are grain/bean casseroles (recipes in vegetarian cookbooks).

Nuts and seeds – Nuts and seeds, either raw or roasted without salt or sugar. To prevent rancidity, nuts and seeds should be kept in an air-tight container in the refrigerator. May also use nut butters from health food stores or from fresh ground nuts (this includes peanut butter if allowed, almond butter, cashew butter, walnut butter, sesame butter, and sesame tahini). Nut butters go well on celery sticks and crackers.

Oils and fats – Sunflower, safflower, olive, sesame, peanut, flaxseed (edible linseed), canola and soy oils. Use coldpressed or expeller-pressed oils (available from health food stores), as they are safer for the heart and blood vessels. Do not use corn oil or “vegetable oil” from an unspecified source, as this is usually corn oil. Soy and sunflower or safflower margarine are OK from an allergy standpoint, but we do not consider margarine a desirable food, as there is evidence it may promote heart disease. It is acceptable to use margarine during the elimination and testing period. However, if you are not allergic to butter, we recommend it instead of margarine, once you have completed food testing. Also suggested are vegetable and bean spreads, instead of butter or margarine.

Snacks – Any food can be eaten as a snack, any time of day. Also suggested are celery, carrot sticks or other vegetables; fruit in moderation (no citrus); unsalted fresh nuts and seeds; Barbara’s Granola Bars (from health food stores); wheat-free cookies (check ingredients). Beverages – Herbs teas (no lemon or orange); spring water in glass bottles or clear plastic, seltzer (salt free); Perrier; pure fruit juices without sugar or additives (dilute 50:50 with water); almond nut milk (Nut Quick); soy milk without corn oil (such as Eden Soy Plain); Cafix, Inka and Roma may be used as coffee substitutes. Tap water contains chlorine, fluoride and other potentially allergenic chemicals. In some cases, distilled or spring water in glass bottles is the only water allowed. This would include water used for cooking. If tap water is eliminated, it should be reintroduced as if it were a test food. Restrictions on the type of water permitted will be made on a case by case basis.

Thickeners – Rice, oat, millet, barley, soy, kuzu or amaranth flours; arrowroot, agar.

Spices and condiments – Salt in moderation; pepper, herbal spices without preservatives, citrus or sugar; garlic, ginger, onions; catsup and mustard from the health food store (without sugar); wheat-free tamari sauce; Bragg liquid aminos; vitamin C crystals in water as a substitute for lemon juice.

Miscellaneous – Sugar-free spaghetti sauce; fruit jellies without sugar or citrus; soups such as split pea, lentil, turkey/vegetable, etc.

GENERAL SUGGESTIONS

Do not restrict your calories! Start with a good breakfast, eat frequently throughout the day, and consume at least 4 glasses of water per day. If you do not eat enough, you may experience symptoms of low blood sugar, such as fatigue, irritability, headache, and too-rapid weight loss. To ensure adequate fiber, eat beans, permitted whole grains, whole fruits and vegetables, homemade vegetable soup, nuts and seeds. Be sure to chew thoroughly, in order to enhance digestion.

Plan your meals for the week. Take a list with you to the health food store. If your schedule is very busy and it is hard to think of what to fix, take some time before starting the diet to make a list of all of your favorite types of foods and possible meal plans. For ideas, look through cookbooks that specialize in hypoallergenic diets. Most meals can be modified easily to meet the requirements of the diet, without changing the meal plan for the rest of your family. When you go to the health food store, ask for assistance in locating “allowed” versions of breads, crackers, cereals, muffins, soups, etc. Some people find it helpful to prepare additional foods on the weekend, to cut down on thinking and preparation time during the week. If you need further assistance or ideas, talk with your diet counselor.

Dining out: Do not hesitate to ask questions or make requests. For instance, you could ask for fish topped with slivered almonds, cooked without added seasoning, butter or lemon. Get a baked potato with a slice of onion on top. Order steak or lamb chops with fresh vegetables, also prepared without added seasonings (with the exception of garlic & plain herbs). Use salad bars that do not use sulfites as a preservative, and bring your own dressing (oil and cider vinegar with chopped nuts/seeds and fresh herbs). Get into the habit of carrying pure water, snacks, seasonings, etc., wherever you go, to supplement your meals or to have something on hand if you start to get hungry.

Withdrawal symptoms: About one in four patients develops mild “withdrawal” symptoms within a few days after starting the diet. Withdrawal symptoms may include fatigue, irritability, headaches, malaise, or increased hunger. These symptoms generally disappear within 2-5 days and are usually followed by an improvement in your original symptoms. If withdrawal symptoms are too uncomfortable, take buffered vitamin C (calcium ascorbate – 1,000 mg in tablet form or 1/4 teaspoon of the crystals, up to 4 times a day) or 3/4 teaspoon of “alkali salts” (2 parts potassium bicarbonate, 1 part sodium bicarbonate) in water as needle, up to 3 times a day for several days. In most cases, withdrawal symptoms are not severe and do not require treatment. It is best to discontinue all of the foods abruptly (“cold turkey”), rather than easing into the diet slowly.

Testing individual foods: It may take 3 weeks for symptoms to improve enough to allow you to retest foods. However, it would be best to test the foods anyway, to rule out hidden offenders. Most patients do improve. Some feel so well on the diet that they decide not to test the foods. This could be a mistake. If you wait too long to retest, your allergies may “settle down” and you will not be able to provoke your symptoms by food testing. Then, you will not know which foods you are allergic to. If reintroducing certain foods causes a recurrence of symptoms, you are probably allergic to those foods.

Food sources for testing. Test pure sources of a food. Example: do not use pizza to test cheese, because pizza also contains wheat and corn oil. Do not use bread to test wheat, as it contains other ingredients. Organic sources are the best to use for testing, as you will not experience interference from pesticides, hormones or other additives which may be used in commercial preparations.

Test one new food each day. If your main symptom is arthritic pain, test one new food every other day. Allergic reactions to test foods usually occur within 10 minutes to 12 hours after ingestion. However, joint pains may be delayed by as much as 48 hours.

Eat a relatively large amount of each test food. For instance, on the day to test milk, add a large glass at breakfast, along with any of the other foods on the “permitted” list. If after one serving, your original symptoms come back, or if you develop a headache, bloating, nausea, dizziness, or fatigue, do not eat that food anymore and place it on your “allergic” list. If no symptoms occur, eat the food again for lunch and supper and watch for reactions. Even if the food is well tolerated, do not add it back into your diet until you have finished testing all of the foods. If you do experience a reaction, wait until your symptoms have improved before testing all of the foods. If you do experience a reaction, wait until your symptoms have improved before testing the next food. If you wake up the next morning with head or joint pain, nausea, or any other suspicious symptom, you may be experiencing a delayed reaction to the food you tested the day before. If you are uncertain whether you have reacted to a particular food, remove it from your diet and retest it 4-5 days later. You do not have to test foods you never eat. Do not test foods you already know cause symptoms.

Foods may be tested in any order. Begin testing on a day you are feeling well (without colds, unusual headaches, flu). Review the list of symptoms to watch for and keep a journal of how you feel.


Dairy test – Test milk and cheese on separate days. You may wish to test several cheeses on different days, since some people are allergic to one cheese but not another. It is usually not necessary to test yogurt, cottage cheese, or butter separately.

Wheat test – Wheatena (with no milk or sugar) or another pure wheat cereal, may add soy or nut milk.

Corn test – Use fresh ears of corn or frozen corn (without sauces or preservatives)

Egg test – Test the whites and yolks on separate days, using hard-boiled eggs.

Citrus test – Oranges, grapefruits, lemons, and limes. Test these individually on four separate days. The lemon and lime can be squeezed into Perrier or seltzer. In the case of orange and grapefruit, use the whole fruit.

Frequently eaten foods – Test tap water, if you have eliminated it, followed by those foods you have restricted (such as foods being consumed more than three times a week).

Optional tests – The following foods and beverages are considered undesirable, regardless of whether or not you are allergic to them. If any of them are not now a part of your diet, or if you are fully committed to eliminating them from your diet, there is no need to test them. However, if you have been consuming any of them regularly, it is a good idea to test them and find out how they affect you. Reactions to these foods and beverages may be severe in some cases. They should be tested only on days that you can afford to feel bad.

Coffee and tea test (separate days) – Do not add milk, non-dairy creamer or sugar. May add soy milk. If you use decaffeinated coffee, test it separately. Coffee, tea, decaffeinated coffee, and decaffeinated tea are separate tests.

Sugar test – Put 4 teaspoons of sugar in a drink or on cereal, or mix with another food. Chocolate test – Use 1-2 tablespoons of pure baker’s chocolate or Hershey’s cocoa powder in a drink or mix with another food.

Alcohol test (test this last) – Beer, wine and hard liquor may require testing on different days, as the reaction to each may be different. Have 2 drinks per test day, but only if you can afford not to feel well that day and possibly the next day.

Food additive test – Buy a set of McCormick’s or French’s food dyes and colors. Put 1/2 teaspoon of each color in a glass. Add one teaspoon of the mixture to a glass of water and drink. If you wish, you may test each color separately.

After the testing if finished, it is time to return to the office for a follow-up visit. When you are within 10 days or so of completing your testing, call the office for an appointment. Bring your journal with you, so you may review your experiences with the doctor.

Suggestions for ongoing self-help, if you are allergic to foods:

Rotation Diets: If you have an allergic constitution and eat the same foods every day, you may eventually become allergic to them. After you have discovered which foods you can eat safely, make an attempt to rotate your diet. A fourday schedule is necessary for some severely allergic patients, but most people can tolerate foods more frequently than every four days. You may eventually be able to tolerated allergenic foods, after you have avoided them for 6-12 months. However, if you continue to eat these foods more frequently than every fourth day, the allergy may return. Use common sense and consume a wide variety of foods. Do not just latch onto a few favorites. If you are rotating foods, be sure to avoid all forms of the food when you are on and “off” day. For instance, if you are rotating corn, be sure to avoid corn chips, corn oil, corn sweeteners, etc., except on the days that you are eating corn and corn products. It is not necessary to do strict food rotation during the elimination and retesting periods.

Watch for other allergic reactions: If you have an allergic constitution, you may be allergic to foods other than those you have eliminated and tested on this diet. Pay attention to what you are eating and if you develop symptoms, review your recent meals and try to identify what may be different in what you have eaten. You can then eliminate that food for two weeks and test it again, to see if you can provoke the same symptoms. Symptoms that may be due to food allergy: General: Fatigue, anxiety, depression, insomnia, food cravings, obesity Infection: Recurrent colds, urinary tract infections, sore throats, ear infections, yeast infections Ear, Nose & Throat: Chronic nasal congestion, postnasal drip, fluid in the ears, Menière’s syndrome Gastrointestinal: Irritable bowel syndrome, constipation, diarrhea, abdominal cramping, ulcerative colitis, Crohn’s disease, gallbladder disease Cardiovascular: High blood pressure, arrhythmia, angina Dermatologic: Acne, eczema, psoriasis, canker sores (aphthous ulcers), hives Rheumatologic: Muscle aches, osteoarthritis, rheumatoid arthritis. Neurologic: Migraines and other headaches, numbness. Miscellaneous: Asthma, frequent urination, teeth grinding, bedwetting, infantile colic. Note: most of these disorders have more than one cause, but food allergy is a relatively common and frequently overlooked cause. Copyright 2014 Natural Terrain Naturopathic Clinic. Dr. Christina Bjorndal

Distorted Automatic Thoughts: A Guide for Patients

Please read the following list of distorted automatic thoughts and circle ones that you recognize in yourself. Please bring this circled sheet to your next appointment with Dr. Chris. It can also be helpful to ask a loved one that is trusted to complete the form on your behalf as sometimes we are not aware of the language we are using because we aren’t always objective about our subjective reality.

1) Mind reading: You assume that you know what people think without having sufficient evidence of their thoughts. “He thinks I’m a loser.”

2) Fortunetelling: You predict the future negatively: Things will get worse or there is danger ahead. “I’ll fail that exam,” or “I won’t get the job,“ or “I won’t get better.”

3) Catastrophizing: You believe that what has happened or will happen will be so awful and unbearable that you won’t be able to stand it. “It would be terrible if I failed.”

4) Labeling: You assign global negative traits to yourself and other. “I’m undesirable,” or “He’s a rotten person.”

5) Discounting positives: You claim that the positive things you or others do are trivial. “That’s what wives are supposed to do so it doesn’t count when she’s nice to me,” or “Those successes were easy, so they don’t matter.”

6) Negative filtering: You focus almost exclusively on the negatives and seldom notice the positives. “Look at all the people who don’t like me.”

7) Overgeneralizing: You perceive a global pattern of negatives on the basis of a single incident. “This generally happens to me. I seem to fail at a lot of things.”

8) Dichotomous thinking: You view events or people in all-or-nothing terms. “I get rejected by everyone,” or “It was a complete waste of time.”

9) Shoulds: You interpret events in terms of how things should be, rather than simply focusing on what is. “I should do well. If I don’t, then I’m a failure.”

10) Personalizing: You attribute a disproportionate amount of blame to yourself for negative events, and you fail to see that certain events are also caused by others. “The marriage ended because I failed.”

11.) Blaming: You focus on the other person as the source of your negative feelings, and you refuse to take responsibility for changing yourself. “She’s to blame for the way I feel now,” or “My parents cause all my problems.”

12) Unfair comparisons: You interpret events in terms of standards that are unrealistic – for example, you focus primarily on others who do better than you and find yourself inferior in the comparison. “She’s more successful than I am,” or “Others did better than I did on the test.”

13) Regret orientation: You focus on the idea that you could have done better in the past, rather on what you can do better now. “I could have had a better job if I had tried,” or “I shouldn’t have said that.”

14) What if?: You keep asking a series of questions about “what if” something happens, and you fail to be satisfied with any of the answers. “Yeah, but what if I get anxious?” or “What if I can’t catch my breath?”

15) Emotional reasoning: You let your feelings guide your interpretation of reality. “I feel depressed; therefore, my marriage is not working out.” Just because you feel anxious doesn’t mean there’s danger.

16) Inability to disconfirm: You reject any evidence or arguments that might contradict your negative thoughts. For example, when you have the thought “I’m unlovable,” you reject as irrelevant any evidence that people like you. Consequently, your thought cannot be refuted. “That’s not the real issue. There are deeper problems. There are other factors.”

17) Judgement focus: You view yourself, others, and events in terms of evaluations as good-bad or superior-inferior, rather than simply describing, accepting, or understanding. You are continually measuring yourself and others according to arbitrary standards, and finding that you and others fall short. You are focused on the judgments of others as well as your own judgements of yourself. “I didn’t perform well in college,” or “If I take up tennis, I won’t do well,” or “Look how successful she is. I’m not successful.”

The Dirty Dozen & The Clean 15

If you’ve ever wondered which fruits and vegetables are most contaminated with pesticides, the Environmental Working Group (EWG) has answers. Its annual Shopper’s Guide highlights the Dirty Dozen which can help consumers reduce exposure to potentially harmful chemicals while still eating plenty of produce. According to them, below are the 12 fruits and veggies in 2026 that were deemed to be “most contaminated with pesticides.”

Alternatively, the Clean Fifteen helps consumers make informed choices about which produce they can buy non-organic if they want to reduce pesticide exposure while managing grocery costs. It complements the Dirty Dozen, and often includes items with thick skins, peels, or husks, which naturally protect the edible portion from pesticide contamination.

Want to learn more?  Take our Environmental Quiz! Discover how much your environment may be impacting your health — and what you can do to support your body. This quiz only takes 3–5 minutes. You’ll get personalized results and next steps at the end. Take the Quiz Here!

The Importance of an Alkaline Diet

Modern agriculture and food preservation methods have seriously damaged the human diet. The detrimental effects on the human body caused by acidic wastes from processed food and chemical additives are numerous. Acidic byproducts of the foods we eat are the common denominator in all degenerative disease. When acidic wastes accumulate, they can cause organs to malfunction and break down. Balancing the body’s acid-alkaline pH factor is an important way to improve health. For necessary reactions and functions to occur in our body, it must be have a proper pH balance. The internal chemical environment of our bodies is maintained at a pH of approximately 7.0 – which is alkaline. Maintenance of this state is a dynamic process mediated in each moment by numerous reactions that produce acid by-products. Our organs (such as our lungs, kidneys, intestines, and skin) primarily control this internal equilibrium. The body needs oxygen, water, alkaline reserves and acid-buffering minerals to accomplish pH balance.

When an alkaline environment is maintained in the body it is able to function optimally. The acid-forming by-products of stress, inflammation and a poor diet are neutralized only when sufficient mineral-buffering reserves are present. Mineral buffering reserves are the gift that alkaline-forming foods give to our body. A diet that is predominantly alkaline forming is essential to the maintenance of sustained health. Most fruits and vegetables contain higher proportions of alkaline-forming elements than other foods.

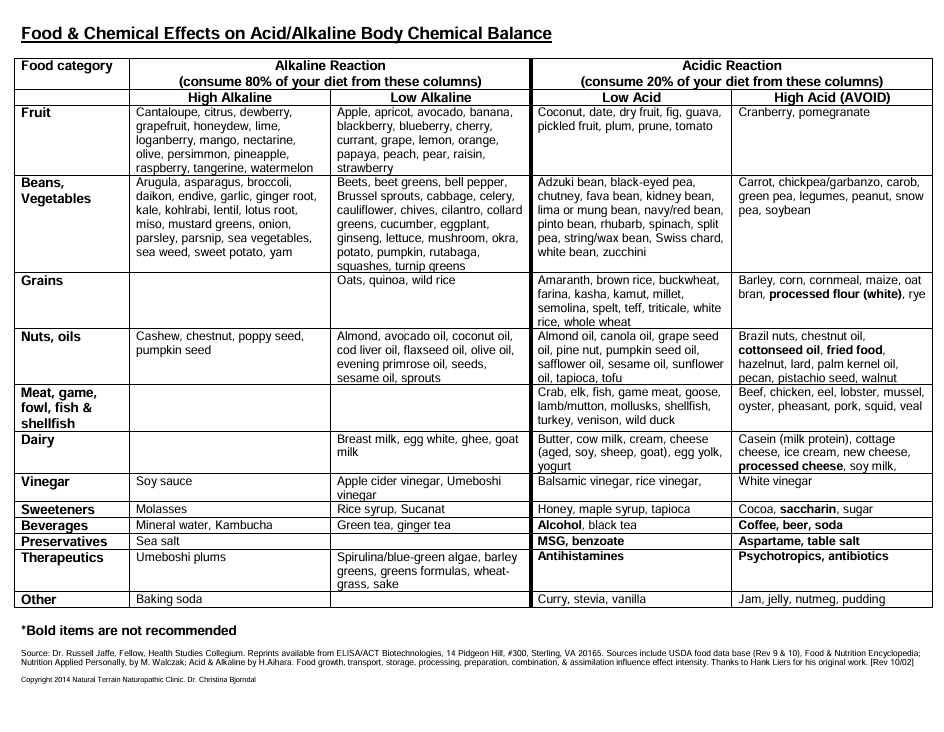
Large amounts of protein and fat promote acid-forming elements; therefore, cow’s milk and dairy products are acid forming. An exception is clarified butter (known as “ghee” in Indian cookery), which has alkalinizing short chain fats known as butyrates and caprylates. The butyrates and caprylates present in ghee are also thought to promote healthy bacterial growth in the intestines, help repair of the intestinal wall and decrease the growth of harmful bacteria, yeast and parasites. On the next page is a chart which categorizes foods as acid or alkaline forming based on how the food is metabolized in the body. In general, fruits, vegetables, lentils, seeds, sprouts, roots and tubers are alkalinizing.

On the other hand, grains, grasses, fowl, fish, seafood, dairy products, meats and most beans are acidifying. To remember this, consider that if a food comes from under or near the ground, it is likely to be alkalinizing. If it comes from on or high above the ground, it is likely to be acid forming.


Tips For Alkalinizing Your Diet


1. Increase consumption of vegetables and fruits as most are alkalinizing

2. Add freshly squeezed lemon or lime juice (¼ – ½ a wedge) in water as a beverage (note: do not put lemon peel in water to avoid drinking pesticides on the peel) & drink lots of pure water.

3. Have 1 cup of alkalinizing greens daily, such as kale, collards, mustard green, rapini, spinach, etc.

4. Eat less acid-forming grains, (wild rice and quinoa instead of wheat and white rice).

5. Learn to make a miso broth (1 tsp of miso dissolved in one cup of hot (not boiling) water). Experiment with adding cooked daikon radish rounds and a small amount of cooked wakame seaweed to the miso broth

6. Make blender drinks using alkaline juices, green powdered supplements and fruit

7. Choose fish and lamb over beef and chicken for less acid forming animal protein

8. Use olive oil as it is less acid forming than other vegetable oils

9. Use buffered Vitamin C to alkalinize the system

10. Practice deep breathing – as oxygen is alkalinizing to the body

11. Ensure alkaline forming foods comprise 80% of your diet and acid forming foods 20% of your diet (see chart on reverse)

The 6 “R’s” of Working with Problematic Thought Patterns

Thought patterns can get us into lots of trouble!  They can have a tremendous “stickiness” that gets our minds “stuck” around certain issues, beliefs or concepts. Once our minds are “stuck” we humans feel a tremendous “urge” to follow these thought patterns… which often times, doesn’t lead anywhere good. This is an overview of working with this “sticky” quality of our minds, and freeing ourselves of the “urge” to follow destructive patterns.

1. Recognizing 

  • Recognize that you are stuck!!
  • The 1st and most important step.
  • A useful quote that can help us out here is… “the emotions are our bodies reaction to thought”
  •  Chances are that if you are feeling strong emotions, you are probably “stuck” somewhere.


2. Refraining

  • Refrain from following the “urge” to follow destructive thinking patterns.
  • I find it useful to do something other than the usual response here…
  • If you know “The Work” then this would be a great time to do it!
  • By refraining we train ourselves to adapt and respond more appropriately to life


3. Relaxing

  •  Once we refrain from our habitual “urge” to follow, we may find that the feeling of being stuck is still there… this is normal.
  • Relax into the feeling of being “stuck”
  • You will find that if you can allow yourself to relax, both the feeling and the urge to follow our habitual responses dissipate and lessen!
  • I find it useful to practice a breathing exercise or grounding practice (like meditation) to allow this relaxation to occur.


4. Resolve

  • Resolve to do this process again and again!
  • Why? Because you are human, and it’s in the nature of humans to get stuck in problematic thinking patterns from time to time!
  • Don’t be harsh on yourself with this… Don’t say to yourself “Oh jeez… here I am stuck again” in a negative way when you notice that you are stuck. Rather, congratulate yourself for noticing and having the ability to see that you are stuck! This leads to the road of release.


5. Rephrase/Reaffirm:

  • Rephrase whatever the “negative” thought was that your recognized was keeping you stuck
  • Be careful how you talk to yourself because you are listening
  • Complete a “thought record” from Mind over Mood if necessary


6. Reward

  • Treat yourself kindly by rewarding yourself with a simple life pleasure, such as a massage, a nice warm bath or to curl up with a good book.

Energy Givers vs Energy Robbers

Everyone has positive and negative influences in their life. The important thing is to recognize which people, events or situations fill you up and which ones deplete you. By finding out what is stressful for oneself, changes can be made in the right direction towards a more healthful life.

A helpful exercise is to take a piece of paper and divide it into two columns.

Good for me (gives me energy, happiness, health – energy givers) Bad for me (drains my energy and health – energy robbers)
1.

2.

3.

4.

5.

1.

2.

3.

4.

5.

There may be relationships, time commitments, people, work situations, eating patterns that go in one or both columns. You may love a job or commitment (column 1) but not the time commitment associated with it (column 2). By doing this exercise, you can find out what the energy givers are as well as the drainers and can identify the top 5 in each column. In the “bad” column, identify why the top 5 entries are so tough and understand clearly what is going on to have a clear picture of life situations that are negatively affecting your health. See how these prevent you from living a healthy life. Choose the worst one from the “bad” column and make a commitment to eliminate this from your life. Work out a plan to do this. Once this item is eliminated, move onto the next and repeat the exercise.

Looking at circled items from the “good” column, devise a way to do these things more frequently in your life, moving from a life with things that render you powerless to things that make you feel more in control, more empowered in life.

Recognize your “energy robbers”, which are things that make you feel drained. Many energy robbers will show up in the “bad” column. These can be bad foods, commitments, a strong scent, a memory, a room or even a person. As an example, an energy robber could be a friend or family member. If you talk to this friend every day, try minimizing your exposure to this person by talking three times a week or even once a week. If this is someone you are very involved with, you could make a signal to that person to let him or her know you feel your energy draining. If it is someone you do not have open communication with (an energy draining sign) you must do what you can on your own and perhaps rethink this relationship.

If it is work or home conditions, the solution may take a bit of creativity. For instance, at work – only phoning back messages at two time intervals in the day instead of being constantly interrupted on the phone.

If you’re still stuck you can change the situation (eliminate the loud noise – telling people to be quiet), change yourself to the situation (wear earplugs with loud noise) or leave the situation (leave the area of the noise).

Copyright 2014 Natural Terrain Naturopathic Clinic. Dr. Christina Bjorndal

Expanding Orthomolecular Medicine Through an Integrative Systems Approach

Reflections on a Case Report of Treatment-Refractory Pediatric OCD

By Richard Z. Cheng, MD, PhD
Editor-in-Chief, Orthomolecular Medicine News Service (OMNS)


Highlights of the Accompanying Case Report

This editorial accompanies the thoughtful case report by Drs. Aarti Midha and Naresh Midha, who describe the successful long-term management of treatment-refractory pediatric obsessive-compulsive disorder (OCD) using a comprehensive . Their careful clinical investigation and nine-year follow-up provide an important opportunity to reflect on the evolving role of orthomolecular medicine in understanding complex chronic disease.

Key observations include:

  • A 5-year-old child developed sudden-onset OCD, anxiety, anger outbursts, and ADHD-like behaviors that responded poorly to conventional psychiatric treatment.
  • An unexpected improvement following antibiotic therapy prompted clinicians to investigate potential infectious, metabolic, and physiological contributors.
  • Comprehensive evaluation identified multiple potentially modifiable abnormalities, including gut dysbiosis, gluten and dairy intolerance, sleep apnea, elevated aluminum levels, genetic polymorphisms affecting methylation and detoxification (MTHFR, GSTM1, and SOD2), and possible chronic dental focal infection.
  • An individualized, multimodal protocol-including dietary modification, gut restoration, targeted nutritional support, methylation support, mitochondrial support, management of sleep apnea, and dental intervention-was implemented.
  • Complete clinical remission of OCD, anxiety, and anger occurred within six months, with ADHD symptoms resolving over the following two years.
  • Nine years later, the patient remains symptom-free, with excellent academic performance and normal extracurricular participation.

Read the Full Article

This editorial accompanies an OMNS case report on treatment-refractory pediatric OCD.

Download the complete PDF below.

⬇️ Download the complete editorial (PDF)

What is driving the disease?

Rather than accepting symptoms as isolated disorders requiring lifelong suppression, orthomolecular medicine seeks to identify and correct the underlying biochemical and physiological disturbances that permit disease to develop.

As with all case reports, this publication should not be interpreted as proof that any single intervention-or even the entire treatment protocol-will produce similar outcomes in other patients. Multiple therapies were introduced over time, and their individual contributions cannot be determined. Yet that is not the principal lesson of this report.

The importance of this case lies in its way of thinking.

For decades, medicine has largely approached complex disorders by assigning a diagnosis and selecting a corresponding therapy. This strategy has been remarkably successful for many acute illnesses. Chronic diseases, however, rarely arise from a single cause. Instead, they often emerge from interactions among nutrition, metabolism, barrier integrity-particularly the gut and blood-brain barriers-immunity, environmental exposures, endocrine regulation, the microbiome, mitochondrial function, sleep, genetics, and lifestyle.

Pediatric OCD may be one example.

Rather than asking only which medication best suppresses obsessive thoughts, we may also ask:

Why did normal brain function become disturbed in the first place? Why are physiological systems no longer functioning optimally? Which of those abnormalities may be reversible?

The strength of this report lies not only in its favorable outcome, but also in the authors’ willingness to investigate beyond conventional diagnostic boundaries and to consider multiple interacting physiological contributors.

These questions also form the foundation of Integrative Orthomolecular Systems Medicine (I-OM Systems Medicine).

Built on the foundations of Orthomolecular Medicine, I-OM Systems Medicine expands this tradition by focusing on identifying the interconnected root drivers of disease, restoring physiological function, and supporting long-term health.

The accompanying case exemplifies this philosophy. Rather than focusing solely on symptom control, the treating physicians systematically investigated multiple physiological contributors-including the gut microbiome, nutrition, metabolism, toxic burden, sleep, and dental health-and addressed them through a comprehensive, individualized treatment strategy.

From this perspective, the accompanying case is not simply a report about OCD. It is a clinical example of an integrative systems approach applied at the bedside.

The child described in this report was treated not only according to diagnosis, but also according to underlying physiology. Multiple potentially reversible contributors were identified and addressed through an integrated treatment strategy.

Whether every intervention was necessary remains unknown. Whether some interventions contributed more than others will require future investigation. Nevertheless, the sustained clinical remission suggests that comprehensive physiological investigation deserves further scientific study.

Medicine advances through observation as well as experimentation. Many transformative ideas begin with careful attention to individual patients whose clinical course challenges prevailing assumptions. Case reports cannot establish causation, but they often generate the hypotheses that later reshape medical practice.

For readers of OMNS, this report also serves as a reminder that orthomolecular medicine has always been more than a collection of nutritional therapies.

At its core, it is a way of thinking-a commitment to understanding the biological foundations of health and disease, correcting physiological dysfunction whenever possible, and supporting the body’s remarkable capacity for recovery.

As biomedical science increasingly embraces systems biology, network medicine, metabolomics, microbiome research, and precision nutrition, the principles that have guided orthomolecular medicine for decades are finding broader scientific expression.

Rather than viewing these developments as separate disciplines, we should recognize them as complementary parts of an evolving framework for understanding human health.

The thoughtful work of Drs. Midha and Midha reminds us that careful clinical observation, combined with a willingness to investigate the biological foundations of disease, can generate important insights that extend well beyond a single patient.

Their report provides an encouraging example of how expanding orthomolecular medicine through an integrative systems approach may open new possibilities for patients with complex chronic disorders.

The future of medicine will likely depend less on finding a single “magic bullet” than on understanding and restoring the interconnected physiological systems that sustain health.

This case invites clinicians to look beyond symptom management, explore the root drivers of disease, and continue advancing orthomolecular medicine through an integrative systems approach.


Reader Discussion and Questions

OMNS welcomes comments, questions, ideas, experiences, and respectful dialogue from readers, patients, healthcare professionals, researchers, and students worldwide.

We encourage participation on OMNS Interactive, where the exchange of knowledge and perspectives helps advance understanding and foster meaningful discussion.

Join the conversation:
https://omns.substack.com


About OMNS Interactive

OMNS Interactive is the discussion and commentary platform of the Orthomolecular Medicine News Service (OMNS).

The original OMNS website remains the official archive of OMNS publications.

Subscribe to OMNS Interactive for future articles, commentary, and discussions:
https://omns.substack.com

Content is provided for educational purposes only and does not constitute medical advice.
Orthomolecular Medicine

Orthomolecular medicine uses safe, effective nutritional therapy to fight illness. For more information: http://www.orthomolecular.org